
Georgette Tew
  • Blog
  • About
  • Contact

Pes Planus Causes, Indicators And Therapy

7/3/2017

 
Overview

Flat Foot

It is rare to find someone who walks with both feet in perfect alignment. A foot that is flat or has a very high arch does not necessarily require treatment unless there is pain. Often we walk on the inside or outsides of our feet, or with our toes or heels rotated inward or outward more than they should be. These atypical walking patterns can cause many problems not just with the feet but also for the whole body as the alignment of the feet sets the foundation for the whole body?s alignment. One of the most common effects of improper alignment is known as flatfoot, or pes planus.

Causes

Over-pronation is a common biomechanical problem that occurs when the arches collapse while walking or standing. This condition hampers our natural walking pattern, causing an imbalance, and leading to wear and tear in other parts of the body with every step we take. Whether you suffer from over-pronation like most of the population, or you have a true flat foot, in both cases your poor walking pattern may contribute to a range of different complaints. As we age, poor aligment of the feet causes very common conditions such as heel pain or knee pain. Over-pronation has different causes. Obesity, pregnancy, age or repetitive pounding on a hard surface can weaken the arch, leading to over-pronation. Over-pronation is also very common with athletes, especially runners, who most of them nowadays use orthotics inside their shoes.

Symptoms

Feet tire easily and become painful and achy, especially around the arch, ankle and heel. Swelling on the inside bottom of your feet. Back and leg pain. Difficulty standing on toes.

Diagnosis

You can test yourself to see if you have flat feet or fallen arches by using a simple home experiment. First, dip your feet in water. Then step on a hard flat surface, like a dry floor or a piece of paper on the floor, where your footprints will show. Step away and examine your foot prints. If you see complete/full imprints of your feet on the floor, you may have fallen arches. However, it?s important to seek a second option from a podiatrist if you suspect you have fallen arches so they can properly diagnose and treat you.

flat feet exercises

Non Surgical Treatment

Custom orthotics are specially designed insoles, which are made for your by prescription. This is done by taking a plaster cast of the foot in its neutral position and is then sent to a laboratory, with your prescription to be made to your exact specifications. The insole then correctly aligns your foot and as a result your body. This will relieve abnormal strain of tissues and structures which can cause pain. For less severe mal-alignments or for sports use a wide variety of temporary insoles.

Surgical Treatment

Adult Acquired Flat Foot

Generally one of the following procedures is used to surgically repair a flat foot or fallen arch. Arthrodesis. One or more of your bones in the foot or ankle are fused together. Osteotomy. Correcting alignment by cutting and reshaping a bone. Excision. Removing a bone or a bone spur. Synovectomy. Cleaning the sheath that covers the tendon. Tendon transfer. Using a piece of one tendon to lengthen or replace another. Arthroereisis. placing a small device in the subtalar joint to limit motion. For most people, treatment is successful, regardless of the cause, although the cause does does play a major role in determining your prognosis. Some causes do not need treatment, while others require a surgical fix.

Prevention

Flatfeet in children are often an inherited family trait, but it may be possible to prevent the condition in some cases. Recent research has shown that there are several social or cultural factors that can cause flatfeet. These factors include the following, obesity, overweight, unnecessary orthopedic treatments, wearing rigid shoes at a young age, In 1992, a study in India of 2300 children aged 4-13 demonstrated a significant difference in the rate of flatfeet among those who wore shoes regularly and those who did not. In this study, wearing inflexible, closed-toe shoes in early childhood was shown to have a negative effect on the normal development of arches. Children who were allowed to go barefoot or who wore light sandals and slippers had a much lower rate of flatfeet. In 1999, a study in Spain of 1181 children aged 4-13 revealed that the use of orthopedic shoes for treatment of flatfeet in children not only failed to correct the problem, but actually worsened the condition by preventing the normal flexing and arch development of bare or lightly protected feet. Finally, in 2006, a study of 835 children aged 3-6 showed significant differences in the rate of flatfeet based on weight, with normal-weight children having lower rates of flatfeet than children who were overweight or obese. Among adults, flatfeet due to injury, disease, or normal aging are not preventable. However, when flatfeet are related to lifestyle factors, such as physical activities, shoe selection, and weight gain, careful attention to these factors may prevent the development of flatfeet.

After Care

Patients may go home the day of surgery or they may require an overnight hospital stay. The leg will be placed in a splint or cast and should be kept elevated for the first two weeks. At that point, sutures are removed. A new cast or a removable boot is then placed. It is important that patients do not put any weight on the corrected foot for six to eight weeks following the operation. Patients may begin bearing weight at eight weeks and usually progress to full weightbearing by 10 to 12 weeks. For some patients, weightbearing requires additional time. After 12 weeks, patients commonly can transition to wearing a shoe. Inserts and ankle braces are often used. Physical therapy may be recommended. There are complications that relate to surgery in general. These include the risks associated with anesthesia, infection, damage to nerves and blood vessels, and bleeding or blood clots. Complications following flatfoot surgery may include wound breakdown or nonunion (incomplete healing of the bones). These complications often can be prevented with proper wound care and rehabilitation. Occasionally, patients may notice some discomfort due to prominent hardware. Removal of hardware can be done at a later time if this is an issue. The overall complication rates for flatfoot surgery are low.

Heel Aches

7/2/2017

 
Overview

Pain At The Heel

Heel pain is unlike most body aches and injuries because heels can?t be immobilized to rest and recover, at least without considerable inconvenience to the sufferer. Heels can?t be isolated and splinted either ,as body weight will continue to aggravate the condition with every step. Heel pain can be devastating if left untreated, eventually impairing the ability to walk comfortably-or at all. Most heel pain comes from tendon problems, though some types can come from bone issues as well.

Causes

As stated above, if biomechanical complaints such as over pronation exist during running then this can lead to planter fascitis and heel pain. Over pronation occurs when there is excessive mobility in the sab-taler joint of the foot which causes hyper mobility of the foot. Conditions such as flat feet can also cause over pronation. This increased mobility adversely affects all the muscles in the foot and can even affect the lower leg, upper leg and cause back pain. The mechanical imbalance is highlighted during running due to the increased forces being applied to the body Runners often complain that the pain increases when they enter the toe off phase of the running cycle as this stretches the muscle away from the heel bone. Apart from over pronation, other causes of planter fascitis are a change of running shoes, dramatic increases in speed work, hill work and mileage.

Symptoms

Symptoms of plantar fasciitis vary, but the classic symptom is pain after rest--when you first get out of bed in the morning, or when you get up after sitting down for a while during the day. The pain usually diminishes after a few minutes of walking, sometimes even disappearing, but the pain is commonly felt again the longer you're on the foot. Fasciitis can be aggravated by shoes that lack appropriate support, especially in the arch area, and by the chronic irritation of long-periods of standing, especially on concrete, by being overweight. It doesn't help that fascia doesn't heal particularly quickly because it has relatively poor circulation (which is why it's white in colour).

Diagnosis

After you have described your foot symptoms, your doctor will want to know more details about your pain, your medical history and lifestyle, including. Whether your pain is worse at specific times of the day or after specific activities. Any recent injury to the area. Your medical and orthopedic history, especially any history of diabetes, arthritis or injury to your foot or leg. Your age and occupation. Your recreational activities, including sports and exercise programs. The type of shoes you usually wear, how well they fit, and how frequently you buy a new pair. Your doctor will examine you, including. An evaluation of your gait. While you are barefoot, your doctor will ask you to stand still and to walk in order to evaluate how your foot moves as you walk. An examination of your feet. Your doctor may compare your feet for any differences between them. Then your doctor may examine your painful foot for signs of tenderness, swelling, discoloration, muscle weakness and decreased range of motion. A neurological examination. The nerves and muscles may be evaluated by checking strength, sensation and reflexes. In addition to examining you, your health care professional may want to examine your shoes. Signs of excessive wear in certain parts of a shoe can provide valuable clues to problems in the way you walk and poor bone alignment. Depending on the results of your physical examination, you may need foot X-rays or other diagnostic tests.

Non Surgical Treatment

Most heel pain is caused by a combination of poor biomechanics, or muscle weakness or tightness. The good news is that heel pain can be effectively managed once the cause is identified. Most heel pain can be successfully treated via pain and pressure relief techniques, biomechanical correction eg orthotics, taping, foot posture exercises, muscle stretches and massage, lower limb muscle strengthening, proprioceptive and balance exercises to stimulate your foot intrinsic muscles. If you feel that your footwear or sports training schedule are potentially causing your heel pain, then we recommend that you seek the advice of a sports physiotherapist, podiatrist or trained footwear specialist (not just a shop assistant) to see if your shoe is a match for your foot; or discuss your training regime to see if you are doing too much. Heel pain and injury are extremely common. With accurate assessment and early treatment most heel pain injuries respond extremely quickly to physiotherapy allowing you to quickly resume pain-free and normal activities of daily living. Please ask you physiotherapist for their professional treatment advice.

Surgical Treatment

It is rare to need an operation for heel pain. It would only be offered if all simpler treatments have failed and, in particular, you are a reasonable weight for your height and the stresses on your heel cannot be improved by modifying your activities or footwear. The aim of an operation is to release part of the plantar fascia from the heel bone and reduce the tension in it. Many surgeons would also explore and free the small nerves on the inner side of your heel as these are sometimes trapped by bands of tight tissue. This sort of surgery can be done through a cut about 3cm long on the inner side of your heel. Recently there has been a lot of interest in doing the operation by keyhole surgery, but this has not yet been proven to be effective and safe. Most people who have an operation are better afterwards, but it can take months to get the benefit of the operation and the wound can take a while to heal fully. Tingling or numbness on the side of the heel may occur after operation.

bestshoelifts

Prevention

Heel Discomfort

Preventing heel pain is crucial to avoid pain that can easily interrupt a busy or active lifestyle. Athletes can prevent damage by stretching the foot and calf both before and after an exercise routine. The plantar fascia ligament can be stretched by using a tennis ball or water bottle and rolling it across the bottom of the foot. With regular stretching, the stretching and flexibility of tissue through the foot can be significantly improved, helping to prevent damage and injury. Athletes should also ease into new or more difficult routines, allowing the plantar fascia and other tissue to become accustomed to the added stress and difficulty. Running up hills is also common among athletes in their routines. However, this activity should be reduced since it places an increased amount of stress on the plantar fascia and increases the risk of plantar fasciitis. Maintaining a healthy weight is also an essential heel pain prevention technique. Obesity brings additional weight and stress on the heel of the foot, causing damage and pain in the heel as well as in other areas of the foot.

Leg Length Discrepancy Shoe Lifts

6/27/2017

 
Overview

Differences of an inch-and-a-half to two inches may require epiphysiodesis (adjusting the growth of the longer side) or acute shortening of the other side. Differences greater than 2.5 inches usually require a lengthening procedure. The short bone is cut and an external device is applied. Gradual lengthening is done over months to allow the muscles and nerves accommodate the new length.Leg Length Discrepancy

Causes

A number of causes may lead to leg length discrepancy in children. Differences in leg length frequently follow fractures in the lower extremities in children due to over or under stimulation of the growth plates in the broken leg. Leg length discrepancy may also be caused by a congenital abnormality associated with a condition called hemihypertrophy. Or it may result from neuromuscular diseases such as polio and cerebral palsy. Many times, no cause can be identified. A small leg length discrepancy of a quarter of an inch or less is quite common in the general population and of no clinical significance. Larger leg length discrepancies become more significant. The long-term consequences of a short leg may include knee pain, back pain, and abnormal gait or limp.

Symptoms

As patients develop LLD, they will naturally and even unknowingly attempt to compensate for the difference between their two legs by either bending the longer leg excessively or standing on the toes of the short leg. When walking, they are forced to step down on one side and thrust upwards on the other side, which leads to a gait pattern with an abnormal up and down motion. For many patients, especially adolescents, the appearance of their gait may be more personally troublesome than any symptoms that arise or any true functional deficiency. Over time, standing on one's toes can create a contracture at the ankle, in which the calf muscle becomes abnormally contracted, a condition that can help an LLD patient with walking, but may later require surgical repair. If substantial enough, LLD left untreated can contribute to other serious orthopaedic problems, such as degenerative arthritis, scoliosis, or lower back pain. However, with proper treatment, children with leg length discrepancy generally do quite well, without lingering functional or cosmetic deficiencies.

Diagnosis

The most accurate method to identify leg (limb) length inequality (discrepancy) is through radiography. It?s also the best way to differentiate an anatomical from a functional limb length inequality. Radiography, A single exposure of the standing subject, imaging the entire lower extremity. Limitations are an inherent inaccuracy in patients with hip or knee flexion contracture and the technique is subject to a magnification error. Computed Tomography (CT-scan), It has no greater accuracy compared to the standard radiography. The increased cost for CT-scan may not be justified, unless a contracture of the knee or hip has been identified or radiation exposure must be minimized. However, radiography has to be performed by a specialist, takes more time and is costly. It should only be used when accuracy is critical. Therefore two general clinical methods were developed for assessing LLI. Direct methods involve measuring limb length with a tape measure between 2 defined points, in stand. Two common points are the anterior iliac spine and the medial malleolus or the anterior inferior iliac spine and lateral malleolus. Be careful, however, because there is a great deal of criticism and debate surrounds the accuracy of tape measure methods. If you choose for this method, keep following topics and possible errors in mind. Always use the mean of at least 2 or 3 measures. If possible, compare measures between 2 or more clinicians. Iliac asymmetries may mask or accentuate a limb length inequality. Unilateral deviations in the long axis of the lower limb (eg. Genu varum,?) may mask or accentuate a limb length inequality. Asymmetrical position of the umbilicus. Joint contractures. Indirect methods. Palpation of bony landmarks, most commonly the iliac crests or anterior iliac spines, in stand. These methods consist in detecting if bony landmarks are at (horizontal) level or if limb length inequality is present. Palpation and visual estimation of the iliac crest (or SIAS) in combination with the use of blocks or book pages of known thickness under the shorter limb to adjust the level of the iliac crests (or SIAS) appears to be the best (most accurate and precise) clinical method to asses limb inequality. You should keep in mind that asymmetric pelvic rotations in planes other than the frontal plane may be associated with limb length inequality. A review of the literature suggest, therefore, that the greater trochanter major and as many pelvic landmarks should be palpated and compared (left trochanter with right trochanter) when the block correction method is used.

Non Surgical Treatment

The way in which we would treat a LLD would depend on whether we have an anatomical or functional difference. To determine which one is causing the LLD you will need to get your legs measured. This is the easiest way to determine if it is anatomical or functional. With a functional LLD we must first determine the cause and treat the cause. Should the cause be one that is not correctable then we may need to treat the LLD as if it were an anatomical or may have to treat the opposite leg to improve one's gait. As for the anatomical LLD, we may start off with a heel lift only in the shoe and follow up to see if we will need to put the lift full sole on the bottom of the shoe. This is determined by the affects that a heel lift in one shoe may have on that knee. Should the LLD be more than 1/4 inch we usually recommend starting between 1/8 inch to 1/4 inch less than the actual amount and let the body adjust to the change and then raise up to the measured amount later.

Leg Length

what shoes make you taller

Surgical Treatment

Surgeries to lengthen a leg are generally only performed when there is a difference in leg length of greater than four centimeters. These types of surgeries can be more difficult and have more complications, such as infections, delayed healing, dislocations, and high blood pressure. In a several step process, bone lengthening surgeries involve cutting a bone in two in order to allow new bone growth to occur. After the bone is cut, a special apparatus is worn with pins that will pull the bone apart at approximately one millimeter per day. This causes osteogenesis, or new bone growth, in between the cut bone segments. A cast or brace may be required for several months after surgery to allow the new bone growth to harden and provide extra support.

Leg Length Discrepancy Surgery Recovery

6/26/2017

 
Overview

Leg shortening is employed when LLD is severe and when a patient has already reached skeletal maturity. The actual surgery is called an osteotomy , which entails the removal of a small section of bone in the tibia (shinbone) and sometimes the fibula as well, resulting in the loss of around an inch in total height. Leg lengthening is a difficult third option that has traditionally had a high complication rate. Recently, results have improved somewhat with the emergence of a technique known as callotasis , in which only the outer portion of the bone (the cortex ) is cut, (i.e. a corticotomy ). This allows the bone to be more easily lengthened by an external fixation device that is attached to either side of the cut bone with pins through the skin. The ?ex-fix,' as it is sometimes called, is gradually adjusted by an orthopaedic surgeon, and healing can occur at the same time that the leg is being distracted , or lengthened over time. Unlike epiphysiodesis, leg lengthening procedures can be performed at almost any skeletal or chronological age.Leg Length Discrepancy

Causes

Limb-length conditions can result from congenital disorders of the bones, muscles or joints, disuse or overuse of the bones, muscles or joints caused by illness or disease, diseases, such as bone cancer, Issues of the spine, shoulder or hip, traumatic injuries, such as severe fractures that damage growth plates.

Symptoms

Often there are few or no symptoms prior to the age of 25-35. The most common symptom is chronic lower back pain, but also is frequently middle and upper back pain. Same-sided and repeated injury or pain to the hip, knee and/or ankle is also a hallmark of a long-standing untreated LLD. It is not uncommon to have buttock or radiating hip pain that is non-dermatomal (not from a disc) and tends to go away when lying down.

Diagnosis

The doctor carefully examines the child. He or she checks to be sure the legs are actually different lengths. This is because problems with the hip (such as a loose joint) or back (scoliosis) can make the child appear to have one shorter leg, even though the legs are the same length. An X-ray of the child?s legs is taken. During the X-ray, a long ruler is put in the image so an accurate measurement of each leg bone can be taken. If an underlying cause of the discrepancy is suspected, tests are done to rule it out.

Non Surgical Treatment

The object of treatment for leg length discrepancy is to level the pelvis and equalize the length of the two limbs. Inequalities of 2-2.5 centimeters can be handled with the following. Heel lifts/ adjustable heel lifts can be used inside a shoe where shoes have a full heel counter. Heel lifts may be added to the heel on the outside of the shoe along with an internal heel lift. Full platforms along the forefoot and rearfoot area of a shoe can be added. There are many different adjustable heel lifts available on the market. For treatment of a leg length discrepancy, consult your physician. They may refer you to a Physiotherapist or Chiropractor for determination of the type of LLD. A Certified Pedorthist (Canada) will treat a structural leg length discrepancy with a heel lift or in larger discrepancies a footwear modification.

Leg Length Discrepancy Insoles

shoe lifts for women's shoes

Surgical Treatment

Surgery to shorten the longer leg. This is less involved than lengthening the shorter leg. Shortening may be done in one of two ways. Closing the growth plate of the long leg 2-3 years before growth ends (around age 11-13), letting the short leg catch up. This procedure is called an epiphysiodesis. Taking some bone from the longer leg once growth is complete to even out leg lengths. Surgery to lengthen the shorter leg. This surgery is more involved than surgery to shorten a leg. During this surgery, cuts are made in the leg bone. An external metal frame and bar are attached to the leg bone. This frame and bar slowly pull on the leg bone, lengthening it. The frame and bar must be worn constantly for months to years. When the frame and bar are removed, a leg cast is required for several months. This surgery requires careful and continued follow-up with the surgeon to be sure that healing is going well.

Addressing Mortons Neuroma

6/5/2017

 
Overview

plantar neuromaMorton's neuroma is an enlarged nerve that usually occurs in the third interspace, which is between the third and fourth toes. To understand Morton's neuroma further, it may be helpful to look at the anatomy of the foot. Problems often develop in the third interspace because part of the lateral plantar nerve combines with part of the medial plantar nerve here. When the two nerves combine, they are typically larger in diameter than those going to the other toes. Also, the nerve lies in subcutaneous tissue, just above the fat pad of the foot, close to an artery and vein. Above the nerve is a structure called the deep transverse metatarsal ligament. This ligament is very strong, holds the metatarsal bones together, and creates the ceiling of the nerve compartment. With each step, the ground pushes up on the enlarged nerve and the deep transverse metatarsal ligament pushes down. This causes compression in a confined space.

Causes

Poorly fitted footwear can be a cause. Shoes that have a tight and narrow toe box can cause the never to become entrapped causing the pain. High heeled shoes abnormally place the metatarsals under extreme pressure which can cause Morton?s Neuroma. In cases of abnormal pronation, there can be significant motion between the 3rd and 4th metatarsals which can cause an irritation to the nerve that runs between them. This inflammation causes the pain.

Symptoms

If you have a Morton's neuroma, you will probably have one or more of these symptoms. Tingling, burning, or numbness. A feeling that something is inside the ball of the foot, or your sock is bunched up. Pain that is relieved by removing your shoes. A Morton's Neuroma often develops gradually. At first the symptoms may occur only occasionally, when wearing narrower shoes or performing certain activities. The symptoms may go away temporarily by massaging the foot or by avoiding aggravating shoes or activities. Over time the symptoms progressively worsen and may persist for several days or weeks. The symptoms become more intense as the neuroma enlarges and the temporary changes in the nerve become permanent.

Diagnosis

Your podiatric physician will begin by taking a history of your problem. Assist him or her by describing your condition as well as you can. Keep track of when the symptoms started and how, any changes you?ve noted (whether the pain has gotten worse, or whether other symptoms have appeared as well, etc.). If you?ve noticed that certain activities or footwear make things worse or bring about additional symptoms, be sure to mention that. If you work in specific footwear, or if you participate in any certain sports, bring the shoes you use. Your doctor may be able to learn quite a lot about your condition that way!

Non Surgical Treatment

Sclerosing alcohol injections are an increasingly available treatment alternative if the above management approaches fail. Dilute alcohol (4%) is injected directly into the area of the neuroma, causing toxicity to the fibrous nerve tissue. Frequently, treatment must be performed 2-4 times, with 1-3 weeks between interventions. An 60-80% success rate has been achieved in clinical studies, equal to or exceeding the success rate for surgical neurectomy with fewer risks and less significant recovery. If done with more concentrated alcohol under ultrasound guidance, the success rate is considerably higher and fewer repeat procedures are needed. Radio Frequency Ablation is also used in the treatment of Morton's Neuroma The outcomes appear to be equally or more reliable than alcohol injections especially if the procedure is done under ultrasound guidance.intermetatarsal neuroma

Surgical Treatment

Recently, an increasing number of procedures are being performed at specialist centers under radiological or ultrasound guidance. Recent studies have shown excellent results for the treatment of Morton's neuroma with ultrasound guided steroid injections, ultrasound guided sclerosing alcohol injections, ultrasound guided radiofrequency ablation and ultrasound guided cryo-ablation.

Prevention

Ensuring that shoes are well fitted, low-heeled and with a wide toe area may help to prevent Morton's neuroma.

Hammer Toe Straightening Surgery

7/4/2015

 
HammertoeOverview
A hammertoe is a toe that's curled due to a bend in the middle joint of a toe. Mallet toe is similar, but affects the upper joint of a toe. Otherwise, any differences between Hammertoes and mallet toe are subtle. Both hammertoe and mallet toe are commonly caused by shoes that are too short or heels that are too high. Under these conditions, your toe may be forced against the front of your shoe, resulting in an unnatural bending of your toe and a hammer-like or claw-like appearance. Relieving the pain and pressure of hammertoe and mallet toe may involve changing your footwear and wearing shoe inserts. If you have a more severe case of hammertoe or mallet toe, you may need surgery to experience relief.

Causes
Claw, hammer and mallet toe are most commonly caused by wearing high heels or ill-fitting shoes that are too tight e.g. narrow toebox. If shoes like this are worn for long periods, the foot is held in a slightly bent position and gradually over time, the muscles tighten and shorten. If this continues for long enough, then the muscles become so tight that even when shoes are removed, the toe is still held in the bent position. Another common cause is Morton?s Toe, where the second toe is longer than the big toe. In this case, the second toe is commonly squashed into a shoe into an unnaturally bent position. Hammer Toe

Symptoms
Well-developed hammertoes are distinctive due to the abnormal bent shape of the toe. However, there are many other common symptoms. Some symptoms may be present before the toe becomes overly bent or fixed in the contracted position. Often, before the toe becomes permanently contracted, there will be pain or irritation over the top of the toe, particularly over the joint. The symptoms are pronounced while wearing shoes due to the top of the toe rubbing against the upper portion of the shoe. Often, there is a significant amount of friction between the toe and the shoe or between the toe and the toes on either side of it. The corns may be soft or hard, depending on their location and age. The affected toe may also appear red with irritated skin. In more severe cases, blisters or open sores may form. Those with diabetes should take extra care if they develop any of these symptoms, as they could lead to further complications.

Diagnosis
Your doctor is very likely to be able to diagnose your hammertoe simply by examining your foot. Even before that, he or she will probably ask about your family and personal medical history and evaluate your gait as you walk and the types of shoes you wear. You'll be asked about your symptoms, when they started and when they occur. You may also be asked to flex your toe so that your doctor can get an idea of your range of motion. He or she may order x-rays in order to better define your deformity.

Non Surgical Treatment
Many people start by treating the problem themselves when they have a painful corn or callus. They try to remove the corn by cutting it off or by applying strong acids, and they try to cushion the toe by applying cushioned pads. Because these treatments can be difficult to perform by oneself (and should never be done by oneself when the patient is diabetic or circulation is poor), and because these treatments only treat the symptom, not the structural deformity that causes their symptom, these treatments can often provide only limited success, and often any success is for only short periods of time. Changes in shoe choices and various types of paddings and other appliances may help, too. For longer-lasting help, we must examine the cause of the deformity. The reason for knowing the cause is that the type of treatment will vary, depending upon the cause of the complaint. Orthotics help control the causes of certain types of contracted toes, (those caused by flexor stabilization, for example), but not other types.

Surgical Treatment
If you are unable to flex your toe, surgery is the only option to restore movement. Surgery is used to reposition the toe, remove deformed or injured bone, and realign your tendons. Surgery is normally done on an outpatient basis, so you can return home on the day of your surgery. Hammertoe

Prevention
What to do after you wear your high heels to avoid getting the hammertoes has to do with stretching and opening up the front of the foot. There?s a great product called Yoga Toes that you can slide on your foot and it will stretch and open up all of the toes, elongating and stretching the muscles in the front of the foot. I also advise people to stretch the back of their legs, which is the calf muscle, which puts much less pressure on the front of the foot. The less pressure you have on the front of the foot, the less the foot will contract in and start creating the hammertoes.

Why Do I Have Bunions?

6/6/2015

 
Overview
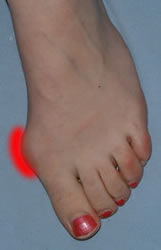
Bunion Pain The common bunion is a localized area of enlargement of the inner portion of the joint at the base of the big toe. The enlargement actually represents a misalignment of the big toe joint (metatarsal phalangeal joint) and, in some cases, additional bone formation. The misalignment causes the big toe to point outward (medically termed hallux valgus deformity) toward the smaller toes. This deformity is progressive and will increase with time. The enlarged joint at the base of the big toe (the first metatarsophalangeal joint, or MTP joint) can become inflamed with redness, tenderness, and pain. A small fluid-filled sac (bursa) adjacent to the joint can also become inflamed (bursitis), leading to additional swelling, redness, and pain. A more deep joint pain may occur as localized arthritis develops in later stages of the deformity. A less common bunion is located at the joint at the base of the smallest (fifth) toe. This bunion is sometimes referred to as a tailor's bunion or bunionette.
Causes
Women tend to get bunions more than men. This could be due to the more restrictive footwear they wear, (such as high heels or narrow toe boxes which force the big toe towards the little toes) but women also tend to have looser ligaments, making them slightly more prone. You?re also more likely to get bunions if your parents or grandparents have them.

Symptoms
Just because you have a bunion does not mean you have to have pain. There are some people with very severe bunions and no pain and people with mild bunions and a lot of pain. Symptoms for a bunion may include pain on the inside of your foot at the big toe joint. Swelling on the inside of your foot at the big toe joint. Redness on the inside of your foot at the big toe joint. Numbness or burning in the big toe (hallux). Decreased motion at the big toe joint. Painful bursa (fluid-filled sac) on the inside of your foot at the big toe joint. Pain while wearing shoes, especially shoes too narrow or with high heels. Joint pain during activities. Other conditions which may appear with bunions include corns in between the big toe and second toe. Callous formation on the side or bottom of the big toe or big toe joint. Callous under the second toe joint. Pain in the second toe joint.

Diagnosis
A doctor can very often diagnose a bunion by looking at it. A foot x-ray can show an abnormal angle between the big toe and the foot. In some cases, arthritis may also be seen.

Non Surgical Treatment
Sometimes observation of the bunion is all that's needed. A periodic evaluation and x-ray examination can determine if your bunion deformity is advancing, thereby reducing your chance of irreversible damage to the joint. In many other cases however some type of treatment is needed. Early treatments are aimed at limiting the progression of the deformity and easing the pain of the bunion or an associated joint. Conservative treatments such as orthotics can achieve this but they won't reverse the deformity itself. These options include changes in shoe wear. Foot Mechanics Podiatrists are experts in shoe recommendation. Padding. Pads placed over the area of the bunion can help minimise pain, but will not stop the progression of the bunion. Activity modifications. Avoid activity that causes bunion pain, this could include standing for long periods of time. Medications. Non-steroidal anti-inflammatory drugs (NSAIDs), such as ibuprofen may help to relieve pain. Icing. Applying an ice pack several times a day helps reduce inflammation and pain. Orthotic devices. Orthotics are the mainstay of non-surgical treatment for bunions. Bunions Hard Skin

Surgical Treatment
For those whose bunions cause persisting pain, a surgical operation is considered for correction of the bunion. The surgical operation to correct a bunion is referred to as a bunionectomy. Surgical procedures can correct deformity and relieve pain, leading to improved foot function. These procedures typically involve removing bony growth of the bunion while realigning the big toe joint. Surgery is often, but not always, successful; failure to relieve pain can result from the big toe moving back to its previous deviated position even after surgery. However, proper footwear and orthotics can reduce the chances of surgical failure.

Prevention
If you are genetically at risk, not a lot. But shoes that are too narrow, too tight (even ballet flats) or have very high heels that force your toes down into the pointed end are asking for trouble. Aim for a 1cm gap between your toes and the end of your shoes. This doesn?t mean wearing frumpy flatties, the Society of Podiatrists and Chiropodists recommends sticking to 4cm heels for everyday wear, and wearing different types of shoe to vary the position of your foot. Gladiator styles can help because the straps stop your foot pushing down into the point of the shoe, ditto Mary Janes (sorry but for beautiful feet they need to have a strap), and flat, wide-fitting brogues are a no-brainer. Alternatively, in summer you can wear flip-flops to keep the space between your big and second toe as wide as possible. If you have children it?s vital to make sure that their feet are measured for properly fitting shoes to nip any potential problems in the bud. Keeping your feet and lower legs supple and strong is important too, that?s how A-list celebs get away with wearing killer heels, they all work-out like crazy. Exercises like trying to widen the space between your big toe and the second one with your foot flat on the floor, a few times a day can help, as can calf stretches. If you are devoted to any exercise that involves high impact for your feet, it might be worth checking that your gait and shoes are correct with a specialist shop such as Runners Need, as poor styles can cause irreparable bunion-related problems that will consign your trainers to the back of the cupboard for ever.

What Causes Overpronation Of The Feet

5/29/2015

 
Overview

Overpronating is a term that is thrown around loosely, whether it be a clinician?s office (PT, Ortho Doc, Podiatrist), in print publication, online, or at your local shoe shop.Being classified as an overpronator is fairly subjective. There?s no criteria to classify you as a runner who overpronates. Pronation is completely normal. Pronation allows your foot to unlock and distribute force up the chain (leg). Pronation that fails to occur, whether it be due to an orthotic, bony structure (high arch), or motion control shoe, may actually increase ground reaction forces (impact). It should make sense, too. Blocking your foot from pronating disengages the first anatomical system for absorbing impact forces. ?Over? insinuates that you pronate too much, but who gets to determine what?s considered normal? We have values that are deemed ?normal,? but varying foot structures complicate the situation. Varying degrees of high, neutral, and low arches all affect this ?normal? pronation number. ?Normal? pronation numbers will simply be out of reach for rigid arches, while flexible feet with surpass the numbers. To dilute the situation further, your strength, habits, and flexibility can all influence how much you pronate.Foot Pronation

Causes

Acquired "Flat Feet" this develops over a period of time rather than at birth (unlike Congenital "Flat Feet"). In children, many different factors may contribute to the development of this condition such as the type of shoes that a child wears, a child's sitting or sleeping positions or it may occur as some type of compensation for other abnormalities located further up the leg. Compensation may occur due to the rupture (tearing) of ligaments or tendons in the foot. One common reason for this condition is that the foot is compensating for a tight Achilles Tendon. If this tendon is tight it may cause the foot to point downward away from the body. This gives the body the perception that the affected leg is longer in length and the body attempts to compensate for the perceived additional length by flattening out the foot arch in an attempt to provide balance and stability.

Symptoms

Because pronation is a twisting of the foot, all of the muscles and tendons which run from the leg and ankle into the foot will be twisted. In over-pronation, resulting laxity of the soft tissue structures of the foot and loosened joints cause the bones of the feet shift. When this occurs, the muscles which attach to these bones must also shift, or twist, in order to attach to these bones. The strongest and most important muscles that attach to our foot bones come from our lower leg. So, as these muscles course down the leg and across the ankle, they must twist to maintain their proper attachments in the foot. Injuries due to poor biomechanics and twisting of these muscles due to over-pronation include: shin splints, Achilles Tendonitis, generalized tendonitis, fatigue, muscle aches and pains, cramps, ankle sprains, and loss of muscular efficiency (reducing walking and running speed and endurance). Foot problems due to over-pronation include: bunions, heel spurs, plantar fasciitis, fallen and painful arches, hammer toes, and calluses.

Diagnosis

Pronounced wear on the instep side of shoe heels can indicate overpronation, however it's best to get an accurate assessment. Footbalance retailers offer a free foot analysis to check for overpronation and help you learn more about your feet.Overpronation

Non Surgical Treatment

The following exercises help retrain the foot and ankle complex to correct overpronation. Step Up and Over. This exercise is designed to integrate skills learned in the Duck Stand, Big Toe Pushdowns and Side Step with Opposite Reach exercises to mimic walking and even running. Using the gluteal muscles and big toe in tandem will prevent overpronation while moving back and forth over the BT in a more effective, balanced motion. Movement Directions. Stand with left foot on top of the BT dome. (Note: For added balance, the right foot can tap on the ground, if needed). Extend right foot backwards to the ground and drop hips into a lunge position. Make sure that the right arm rotates across the left leg (this will activate the gluteal muscles on the left side). Now, step through and over the BT into a front lunge with the right leg forward. While lunging forward, the torso and left arm now rotate over the right leg. Throughout the exercise, push big toe down into the BT. Perform 8 to 10 repetitions on both sides.

Prevention

Custom-made orthotics will reduce the twisting of the leg muscles as they enter the foot, by maintaining a normal alignment of the bones and joints of the foot. If the bones and joints are aligned properly, by reducing the pronation, the muscles can run straight to their attachments in the foot, without twisting to get to these bones. This action of custom-made orthotics will reduce Achilles Tendonitis shin splints; ankle, knee, hip, and lower back pain; and leg cramps. This action will also allow the leg muscles to work more efficiently, thus allowing you to walk and run with less effort.

The Best Way To Treat Calcaneal Apophysitis?

5/15/2015

 
Overview

Sever?s disease is a heel problem that is the most common cause of heel pain that commonly occurs in children. It is caused by repetitive use and overuse of the heel while it is still growing, therefore is more common in active children and teenagers. Despite the name, Sever?s Disease like Osgood- Schlatter disease is caused by overuse and is not a disease.

Causes

There are many contributing factors that cause strain across the growth plate, making your child prone to developing Sever?s disease. These include repeated minor trauma to the growth plate from running or jumping sports, tight calf or hamstring muscles, rapid growth spurts can lead to the leg muscles becoming tight, increasing tension on the growth plate, tight Achilles tendon, the Achilles tendon attaches to the back of the heel adjacent to the growth plate, poor foot posture, may increase the strain on the growth plate, footwear with a very low heel pitch (eg soccer boots), unsupportive or unstable footwear with poor shock absorption at the heel, running or playing sport on hard surfaces.

Symptoms

The symptoms of Sever?s disease occur in the heel and the foot, and may worsen with activity. Pain and stiffness can occur in one or both heels. Symptoms can include. Swelling in the heel. Redness in the heel. Antalgic gait (such as limping). Foot pain or stiffness first thing in the morning or while walking. Pain that is worsened by squeezing the heel.

Diagnosis

Sever disease is most often diagnosed clinically, and radiographic evaluation is believed to be unnecessary by many physicians, but if a diagnosis of calcaneal apophysitis is made without obtaining radiographs, a lesion requiring more aggressive treatment could be missed. Foot radiographs are usually normal and the radiologic identification of calcaneal apophysitis without the absence of clinical information was not reliable.

Non Surgical Treatment

The following are different treatment options Rest and modify activity. Limit running and high-impact activity to rest the heel and lessen the pain. Choose one running or jumping sport to play at a time. Substitute low-impact cross-training activities to maintain cardiovascular fitness. This can include biking, swimming, using a stair-climber or elliptical machine, rowing, or inline skating. Reduce inflammation. Ice for at least 20 minutes after activity or when pain increases. Nonsteroidal anti-inflammatory drugs (NSAIDs) may also help. Stretch the calf. Increase calf flexibility by doing calf stretches for 30 to 45 seconds several times per day. Protect the heel. The shoe may need to be modified to provide the proper heel lift or arch support. Select a shoe with good arch support and heel lift if possible. Try heel lifts or heel cups in sports shoes, especially cleats. Try arch support in cleats if flat feet contribute to the problem. Take it one step at a time. Gradually resume running and impact activities as symptoms allow. Sever?s disease usually goes away when the growth plate (apophysis) matures, which should be by age 12 to 13 years in females and 13 to 14 years in males.

What Will Be The Signs And Symptoms Of An Achilles Tendon Rupture

5/2/2015

 
Overview
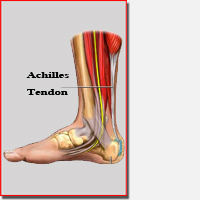
Achilles Tendinitis An Achilles tendon rupture is also known as a rupture of the gastrocnemius tendon, or the common calcanean tendon. The tendon is actually composed of 5 different tendons, the two most important being the superficial digital flexor and gastrocnemius tendons. The gastrocnemius tendon is the largest of these, and is the most powerful extensor of the hock (ankle) joint. Both the superficial digital flexor and gastrocnemius tendons attach to the heel bone, called the calcaneus bone. A rupture of the Achilles tendon may be a partial tear, which means just the gastrocnemius is torn, or a complete tear, in which all five tendons have been torn. (show diagrams, normal anatomy vs partial vs complete tears).

Causes
The exact cause of Achilles tendon ruptures is hard to say. It can happen suddenly, without warning, or following an Achilles tendonitis . It seems that weak calf muscles may contribute to problems. If the muscles are weak and become fatigued, they may tighten and shorten. Overuse can also be a problem by leading to muscle fatigue . The more fatigued the calf muscles are, the shorter and tighter they will become. This tightness can increase the stress on the Achilles tendon and result in a rupture. Additionally, an imbalance of strength of the anterior lower leg muscles and the posterior lower leg muscles may also put an athlete at risk for an injury to the Achilles tendon. An Achilles tendon rupture is more likely when the force on the tendon is greater than the strength of the tendon. If the foot is dorsiflexed while the lower leg moves forward and the calf muscles contract, a rupture may occur. Most ruptures happen during a forceful stretch of the tendon while the calf muscles contract. Other factors that may increase the risk of Achilles tendon rupture include. Tight calf muscles and/or Achilles tendon. Change in running surface eg: from grass to concrete. Incorrect or poor footwear. A change of footwear eg: from heeled to flat shoes. It is thought that some medical conditions, such as gout, tuberculosis and systemic lupus erythematosus, may increase the risk of Achilles tendon rupture.

Symptoms
Symptoms include a sudden sharp pain in the achilles tendon which is often described as if being physically struck by an object or implement. A loud snapping noise or bang may also be heard at the time. A gap of 4 to 5 cm in the tendon can be felt which may be less obvious later as swelling increases. After a short while the athlete may be able to walk again but without the power to push off with the foot. There will be a significant loss of strength in the injured leg and the patient will be unable to stand on tip toes. There may be considerable swelling around the achilles tendon and a positive result for Thompson's test can help confirm the diagnosis.

Diagnosis
The doctor may look at your walking and observe whether you can stand on tiptoe. She/he may test the tendon using a method called Thompson?s test (also known as the calf squeeze test). In this test, you will be asked to lie face down on the examination bench and to bend your knee. The doctor will gently squeeze the calf muscles at the back of your leg, and observe how the ankle moves. If the Achilles tendon is OK, the calf squeeze will make the foot point briefly away from the leg (a movement called plantar flexion). This is quite an accurate test for Achilles tendon rupture. If the diagnosis is uncertain, an ultrasound or MRI scan may help. An Achilles tendon rupture is sometimes difficult to diagnose and can be missed on first assessment. It is important for both doctors and patients to be aware of this and to look carefully for an Achilles tendon rupture if it is suspected.

Non Surgical Treatment
Non-surgical treatment typically involves wearing a brace or cast for the first six weeks following the injury to allow time for the ends of the torn tendon to reattach on their own. Over-the-counter medications, such as ibuprofen or aspirin, may be taken during this time to reduce pain and swelling. Once the tendon has reattached, physical therapy will be needed to strengthen the muscles and tendon. A full recovery is usually made within four to six months. Achilles Tendonitis

Surgical Treatment
Surgery to repair an Achilles tendon rupture is performed under a spinal or general anaesthetic. During surgery the surgeon makes an incision in the skin over the ruptured portion of the tendon. The tendon ends are located and joined together with strong sutures (stitches), allowing the tendon to closely approximate its previous length. The skin is then closed with sutures and the foot is immobilised in a cast or splint, again in the toes-pointed position. Seven to ten days after surgery the cast or splint is removed in order for the sutures in the skin to be removed. Another cast or splint will be applied and will stay in place a further 5 - 7 weeks.
<<Previous
Powered by Create your own unique website with customizable templates.
